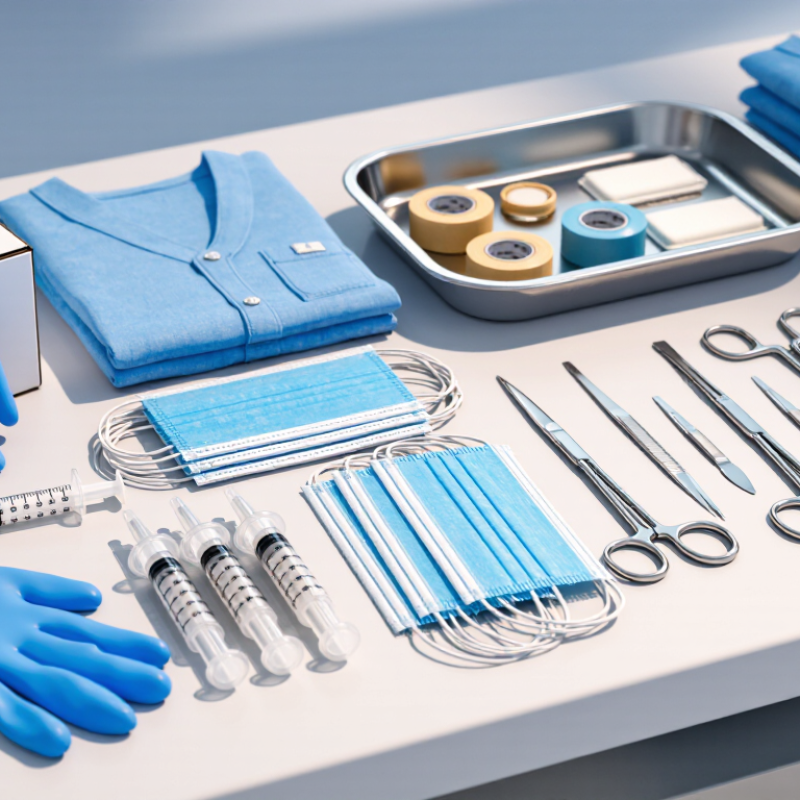
Buying surgical supplies in 2026 requires more than comparing catalog prices. Hospitals, distributors, and clinics need dependable products, clear documentation, and predictable delivery. A low-cost box is not a saving if sterile packaging arrives damaged.
This guide examines practical choices for global buyers, including surgical gloves, gowns, drapes, masks, syringes, wound-care products, and basic instruments. It considers material quality, sterility assurance, ergonomic design, packaging, shelf life, and lot traceability. Supplier evaluation also matters. Buyers should review quality systems, manufacturing records, product specifications, and applicable approvals before placing large orders.
Details matter most.
A reliable supplier should communicate openly about lead times, minimum order quantities, storage conditions, and replacement procedures. For international shipments, buyers must check destination-country requirements rather than assuming one certificate works everywhere. Local regulatory guidance remains essential. Independent inspection can also reduce unpleasant surprises.
No ranking can fit every operating room. A rural clinic may prioritize compact packaging and stable availability. A trauma center may need rapid replenishment and broader sizing. Sustainability deserves attention, but environmental claims should be supported by measurable evidence. Reusable products can reduce waste, yet cleaning capacity and infection-control procedures must be assessed carefully.
We may overlook small issues. A glove may fit poorly. A carton may be difficult to open with wet hands. These details affect real clinical work. The best surgical supplies combine safety, usability, verified quality, and dependable support. This introduction sets a practical foundation for comparing products and suppliers with professional judgment, documented evidence, and appropriate caution.
Surgical supplies are medical products used during preparation, treatment, and recovery. They include sterile gloves, surgical gowns, masks, drapes, gauze, sutures, syringes, and operating instruments. Some are disposable. Others require cleaning, sterilization, and careful maintenance. Each item supports a specific clinical step, so a small quality problem can affect the entire procedure.
Global buyers need these supplies because hospitals, clinics, and emergency teams depend on consistent access. Demand can change quickly during outbreaks, disasters, or seasonal surgery peaks. Buyers must check sterility, material safety, shelf life, packaging strength, and lot traceability. Products should also match local medical-device rules and facility protocols. A low price means little if cartons arrive damaged or labels cannot be verified.
From practical procurement experience, clear documentation often prevents more trouble than aggressive bargaining. Request product specifications, test reports, certificates, storage guidance, and replacement terms. Confirm whether staff can use the product without extra training. Packaging needs attention too. Moisture, heat, and rough transport may damage sterile barriers. Even experienced teams miss details. A checklist helps, but it is not perfect. Buyers should review supplier performance after delivery, including defect rates, lead times, and complaint handling. A reliable supply decision protects clinical work, not just purchasing budgets.
Global surgical-care indicators highlighting the scale of demand for safe, reliable, and affordable surgical supplies.
Global estimates indicate that approximately 313 million surgical procedures are performed each year, while an additional 143 million procedures may be needed annually. Around 5 billion people lack access to safe, affordable surgical and anesthesia care, and approximately 33 million people experience catastrophic health expenditure because of surgery. These indicators demonstrate why global buyers need dependable supplies such as sterile instruments, surgical gloves, gowns, drapes, sutures, wound-care products, and anesthesia-related equipment.
Source: The Lancet Commission on Global Surgery and related global surgery estimates. Figures are rounded and represent global annual estimates reported in the cited research.
Global buyers should classify surgical supplies by clinical function, not product shape alone. This method reduces mismatched orders and supports clearer staff training. Hemostatic supplies control bleeding. Cutting supplies divide tissue. Grasping and retracting instruments hold tissue or improve surgical visibility. Closure supplies bring wound edges together. Short labels help.
Diagnostic and monitoring supplies support assessment before, during, or after surgery. Fluid-management products deliver, collect, or filter liquids. Protective supplies create barriers around patients, staff, and sterile fields. A suction catheter may remove fluid, but its diameter, flexibility, connector, and sterility determine its suitability. One category is rarely enough.
Procurement teams should connect every class with the procedure, tissue type, risk level, and working environment. Check packaging integrity, expiry dates, material compatibility, sterilization method, and instructions for use. Quality records should support traceability and routine inspection. Requirements can differ between a large operating room and a small mobile clinic. That detail is easy to miss. A clean spreadsheet may still hide a clinical mismatch. I have seen product names appear precise while their intended use remained unclear. Buyers should invite feedback from surgeons, nurses, infection-control staff, and warehouse teams before final approval. Mistakes become useful only when teams document them and change the selection process.
Global buyers should judge surgical supplies by measurable safety evidence, not attractive packaging or low prices. The World Health Organization’s Global Patient Safety Action Plan 2021–2030 reports that around one in ten patients experiences harm during healthcare. More than half of this harm is considered preventable. That figure makes material control, sterile-barrier integrity, and traceability purchasing priorities.
Look for documented compliance with relevant standards, including ISO 13485 for quality management and ISO 14971 for risk management. Sterile products should also show validated processes, such as ISO 11135 for ethylene oxide or ISO 11137 for radiation sterilization. Packaging needs clear batch numbers, expiry dates, sterilization indicators, and storage conditions. The WHO Global Guidelines for the Prevention of Surgical Site Infection also stress proper preparation, sterile technique, and controlled operating environments. Supplies cannot compensate for poor clinical practice.
Check the evidence.
A supplier should provide certificates, test reports, technical files, and complaint-response procedures. Samples should be inspected for torn packaging, weak seals, powder residue, and inconsistent sizing. In my experience, small defects often reveal weak production controls. However, certification can create false confidence. ISO 13485 registration does not automatically prove every product performs safely in a real operating room. Buyers should request independent test results, review recall histories where available, and confirm that local regulations accept the stated conformity documents. A practical audit may expose gaps that paperwork hides.
| Supply Category | Common Materials or Configurations | Key Quality and Safety Criteria | Relevant International Standards | Typical Sterilization or Packaging Requirements | Buyer Verification Points |
|---|---|---|---|---|---|
| Surgical Gloves | Natural rubber latex or synthetic polymers such as nitrile or polychloroprene; sterile, powder-free; multiple sizes. | Barrier integrity, freedom from holes, acceptable bioburden, controlled dimensions, adequate tensile properties, and low allergen risk where applicable. | ISO 10282; EN 455 series; ASTM D3577 where applicable. | Validated terminal sterilization; sterile barrier packaging; package integrity and expiry dating supported by stability data. | Review lot-specific test results, sterilization records, size range, powder status, latex declaration, and package seal integrity. |
| Surgical Gowns | Nonwoven polypropylene, polyester, polyethylene-film laminate, or reusable woven textiles; standard or reinforced zones. | Liquid resistance, lint control, seam strength, suitable sleeve and cuff design, adequate coverage, and correct barrier classification. | ANSI/AAMI PB70; EN 13795-1; ISO 22610 for resistance to microbial penetration where applicable. | Disposable gowns require validated packaging and sterilization when labeled sterile; reusable gowns require validated laundering and reprocessing instructions. | Confirm barrier level, test method, critical-zone reinforcement, size chart, seam construction, and intended procedure risk level. |
| Surgical Masks | Multi-layer nonwoven construction with melt-blown filtration media; ear-loop or tie-on designs; fluid-resistant variants. | Bacterial filtration efficiency, particle filtration efficiency, breathing resistance, splash resistance where required, and secure fit. | EN 14683; ASTM F2100; ISO 22609 for synthetic blood penetration testing where applicable. | Usually supplied non-sterile unless specifically validated and labeled sterile; moisture-resistant outer packaging is recommended. | Check filtration and breathing-resistance test reports, fluid-resistance level, ear-loop strength, labeling, and intended use. |
| Surgical Drapes | Disposable nonwoven materials or reusable woven textiles; fenestrated, adhesive, absorbent, or reinforced designs. | Resistance to liquid penetration, low linting, drape integrity, secure positioning, and effective coverage of the sterile field. | EN 13795-1; ISO 22610 where resistance to microbial penetration is claimed. | Sterile barrier packaging for sterile products; reusable products require validated cleaning, disinfection, inspection, and sterilization cycles. | Confirm dimensions, critical-zone performance, absorbency, adhesive compatibility, packaging configuration, and reprocessing limits. |
| Single-Use Syringes | Polypropylene barrel and plunger with elastomer stopper; two-piece or three-piece designs; luer-slip or luer-lock connections. | Accurate volume delivery, leak resistance, smooth plunger movement, secure connection, clear graduation marks, and low extractables. | ISO 7886-1; ISO 10993 series for biological evaluation as applicable. | Commonly supplied sterile and single-use; validated ethylene oxide, radiation, or other suitable sterilization process; tamper-evident sterile packaging. | Verify nominal capacity, graduation accuracy, dead space, connection type, sterility, shelf life, and compatibility with intended medication. |
| Hypodermic Needles | Stainless-steel cannula with polymer hub; a range of gauges, lengths, bevel designs, and connection types. | Cannula sharpness, bevel geometry, dimensional accuracy, hub security, flow performance, corrosion resistance, and absence of visible defects. | ISO 7864; ISO 9626 for stainless-steel needle tubing; ISO 10993 series as applicable. | Sterile, single-use packaging with validated sterilization and a clearly stated gauge, length, lot number, and expiry date. | Check gauge and length tolerances, bevel type, hub compatibility, sterility assurance documentation, and sharps-disposal requirements. |
| Surgical Blades and Scalpels | Stainless-steel blades with standardized handle compatibility; sterile disposable or reusable handle configurations. | Edge sharpness, dimensional consistency, corrosion resistance, secure attachment, surface cleanliness, and safe handling. | ISO 7740; ISO 10993 series as applicable to patient-contacting components. | Sterile single-use blades require validated sterilization and protective packaging; reusable handles require validated cleaning and sterilization instructions. | Confirm blade number, handle fit, material grade, protective cover design, sterile barrier integrity, and disposal controls. |
| Surgical Sutures | Absorbable or non-absorbable; monofilament or braided; synthetic polymers or processed biological materials; with or without attached needles. | Tensile strength, knot security, needle attachment, controlled absorption profile where applicable, tissue response, and surface uniformity. | USP suture monographs; European Pharmacopoeia requirements where applicable; ISO 10993 series for biological evaluation. | Sterile individual packaging with validated sterilization, material identification, suture size, needle code, lot number, and expiry date. | Review tensile-strength data, absorption profile, needle geometry, coating composition, packaging integrity, and storage conditions. |
| Suction Catheters | Medical-grade flexible polymers such as PVC or polyurethane; straight or curved tips; controlled side-eyelet designs. | Atraumatic tip, kink resistance, flow performance, connector security, dimensional accuracy, and radiopacity where required. | ISO 8836; ISO 10993 series for biological evaluation as applicable. | Sterile, single-use packaging with validated sterilization and clear French size, length, material, and expiry information. | Verify external diameter, length, tip design, vacuum compatibility, connector type, DEHP or plasticizer declaration, and sterility. |
| Sterilization Pouches and Packaging | Medical-grade paper, nonwoven materials, coated film, rigid trays, or combinations designed for a specified sterilization process. | Microbial barrier, seal strength, peelability, material compatibility, visual seal inspection, and maintenance of sterility during storage and transport. | ISO 11607-1 and ISO 11607-2; ISO 11140-1 for process indicator markings where applicable. | Packaging must be validated for the intended sterilization method, sealing equipment, distribution conditions, and claimed shelf life. | Request seal-strength data, dye-leak or integrity testing, sterilization compatibility, storage limits, and transport-validation evidence. |
| Sterilization Chemical Indicators | External indicator tape, internal indicator strips, integrators, or emulators designed for steam or other validated sterilization cycles. | Clear and stable endpoint change, correct response to specified process variables, readable batch identification, and resistance to premature deterioration. | ISO 11140-1; process-specific parts of the ISO 11140 series. | Indicators must be stored within the manufacturer’s specified temperature and humidity range and used only for the validated cycle type. | Confirm indicator class or type, intended sterilization process, response conditions, color-change reference, expiry date, and storage requirements. |
For global buyers, comparing surgical supply suppliers starts with evidence, not polished catalogs. Request product specifications, material grades, sterility status, shelf life, lot traceability, and applicable conformity documents. Check whether documents match the exact item and manufacturing site. Ask for recent, redacted batch records when appropriate. A sample can reveal packaging weakness, unclear labeling, or poor seal integrity. Test before scale. Supplier audits should examine quality controls, complaint handling, change notifications, and business continuity. Video calls help, but onsite or independent verification may provide stronger evidence. No review is perfect.
Price comparisons need a shared calculation sheet. Compare unit price, minimum order quantity, tooling, inspection, packaging, insurance, duties, inland transport, and payment terms. A cheaper carton may contain fewer units or require costly relabeling. Ask for currency validity and written adjustment rules. Include the cost of delays. A missed procedure schedule can outweigh a small discount. Request two or three comparable quotations with identical specifications. Avoid choosing from price alone; reliability has measurable value, even when forecasting it remains difficult.
International logistics should be checked before purchase orders are issued. Confirm production lead time, shipping method, transit estimates, export documents, and destination requirements. Clarify who manages customs information and what happens after a damaged delivery. Use moisture protection and temperature controls when required. Track lot numbers from shipment to receiving inspection. Keep a contingency route for port congestion or sudden regulatory changes. A small pilot shipment can expose weak packing or communication early. It may cost more initially. Buyers should record every assumption, then challenge it during regular supplier reviews.
Global buyers should examine surgical supplies beyond price, appearance, and delivery promises. The product must match its intended clinical use, material requirements, size, and performance expectations. Request clear specifications, recent quality records, and batch-level traceability. Vague descriptions create problems later.
Check whether the supplier can provide appropriate conformity documents, test reports, sterilization information, and certificates for the destination market. Confirm that documents match the exact product, not a similar model. Packaging also matters. Inspect seal quality, labeling, lot numbers, expiry dates, and storage instructions. A strong carton should survive humid warehouses and long transport without crushing.
Ask for samples before placing a large order. Test them under realistic handling conditions, including opening, grip, flexibility, and connection strength. Confirm minimum order quantities, production capacity, lead times, payment terms, and replacement procedures in writing. A low quotation may exclude inspection, insurance, or import-related costs. That detail can hurt the budget.
Do not rely on polished photographs. Product consistency matters more. An independent inspection can reveal weak seals, mixed batches, or incomplete labels. However, no checklist is perfect. Buyers should review supplier performance after each shipment and record defects carefully. Small recurring issues often signal larger process weaknesses. A responsible purchasing decision protects clinicians, patients, and the buyer’s long-term supply planning.
2382 Faraday Avenue, Ste 300
Carlsbad, CA 92008
The materials on this website are for your general educational information only. Information you read on this website cannot replace the relationship that you have with your healthcare professional. We do not practice medicine or provide medical services or advice as a part of this website. You should always talk to your healthcare professional for diagnosis and treatment.
©2025 Breg, Inc. All rights reserved. All trademarks and registered trademarks are owned by the copyright holder.